


Intra-Aortic Balloon Pumps (IABP) aka Counter Pulsation Therapy is an intervention
that the Critical Care Provider may be called upon to transport from one facility to another.
Transporting the counter pulsation patient can be a daunting idea if the provider does not
understand the who’s, why’s and what’s of utilizing and monitoring this device. Intra Aortic
Balloon Pumps are placed to achieve three goals: improve coronary perfusion, decrease the
workload of the heart and to increase cardiac output. Critically ill patients that require
mechanical support often benefit from IABP therapy. Cardiogenic shock patients, post cardiac
surgery patients, failed PCI patients awaiting coronary bypass surgery and refractory
ventricular failure patients are all candidates for counter pulsation therapy.
The control console of the IABP device utilizes an inflatable balloon embedded on a
catheter that is inserted through a large artery, frequently the femoral artery located in the
patient’s groin.
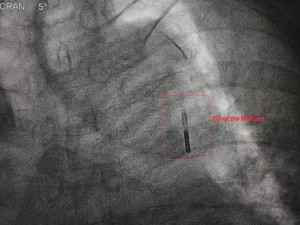
The balloon is inflated and deflated with Helium at specific times and is
located below in the descending aorta below the offshoot of the left subclavian artery and
above the offshoot of the renal arteries. The gas Helium is used due to its lower density and
viscosity compared to other gasses. The lower viscosity allows the the gas to be shuttled back
and forth to the balloon without creating as much heat due to its lower resistance. Helium is
also less likely to create an air embolism if the balloon ruptures or forms a hole. When an IABP
device is properly timed, it inflates just before the aortic valve closes (diastole) and rapidly
deflates just before the aortic valve opens (systole).
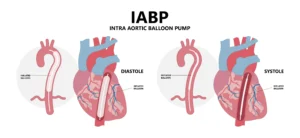
The cardiac muscle fibers are perfused during diastole as the aortic valve closes and the the coronary ostia are exposed and open.
Inflation of the balloon pushes the blood contained in the aorta retrograde back towards the
heart and then into the coronary ostia of the heart. This blood then provides needed oxygen
and nutrients to the cardiac muscle cells or myocytes via the coronary arteries. This action
improves coronary perfusion. Just before systole begins and the aortic valve opens, the
balloon rapidly deflates, creating a vacuum in the aorta. This vacuum assists the left ventricle
with ejecting blood to be transported throughout the body via the systemic circulation. Balloon
deflation at the proper time also will decrease after load (the resistance against which the left
ventricle has to overcome to eject blood). The after load reduction not only improves cardiac
output, it also decreases the overall work of the heart.
Proper timing is essential because if the balloon inflates or deflates too early or too late,
it can actually increase the overall workload of the heart, decrease coronary perfusion and
increase myocardial oxygen demand. Typically the primary trigger for balloon inflation and
deflation is the ECG as it is the most reliable waveform to achieve consistent inflation and
deflation. Pressure triggering is utilized if the patient goes into cardiac arrest and the console
itself will often switch from ECG trigger to pressure trigger if cardiac arrest occurs. The two
most dangerous IABP timing errors are late deflation and early inflation. Late deflation causes
the balloon to remain inflated during the beginning of systole when the aortic valve opens.
Late deflation can increase the overall workload and myocardial oxygen demand as the left
ventricle has to work harder to eject blood against the resistance of the inflated balloon. Early
inflation causes the balloon to inflate before the aortic valve closes and can not only increase
myocardial oxygen demand and workload, it can also potentially damage the aortic valve itself.
Less dangerous timing errors are early deflation and late inflation as both can result in sub
optimal coronary perfusion as well as less improvement in cardiac output. During early
deflation, the balloon deflates before the beginning of systole and does not create a sufficient
vacuum to suck the blood out of the left ventricle when the aortic valve opens. Late inflation
occurs when the balloon inflates after the aortic valve opens rather than just before it opens.
This timing error does not allow the blood to travel back towards the heart and perfuse the
cardiac muscle as effectively.
Patients who are receiving counter pulsation therapy during transport can have very
complex needs. Counter pulsation therapy, while very effective in not only increasing coronary
perfusion pressures but also decreasing the workload of the heart and decreasing myocardial
oxygen demand, must be implemented and timed appropriately. Timing errors can diminish
the effectiveness of the therapy and some can prove dangerous, if not fatal, to these critically ill
patients. Understanding of how and why this intervention works will assist the Critical Care
Provider with not only assessment and management of the patient, but also help with trouble
shooting if something goes wrong.
